
Clinics that cannot hire doctors now have a legal alternative, but only if they already have some. Since 1 October, physician associates have been a regulated health profession under the Medical Council of New Zealand (MCNZ). The new rules give practice owners a real productivity lever. They also tie that lever to the scarcest resource in the system, which is senior doctors with time to spare.
For rural and provincial practices the opportunity is genuine. For anyone hoping PAs will let them run a lean, doctor-light clinic chain, the regulator has already closed that door.
A workforce built for places doctors won’t go
The case for PAs has always rested on recruitment. In 2025, then-Gore Health chief executive Dr Karl Metzler put it bluntly: “If I advertise for a New Zealand doctor in Gore, I get zero applicants. If I advertise for a physician associate, I will get at least 20 applicants.”
The pressure behind that is structural. Royal NZ College of General Practitioners data cited back in 2024 showed 44% of GPs intended to retire within 10 years. MCNZ’s annual report for the year to June 2025 found 43.5% of the medical workforce were international medical graduates. New Zealand already runs its health system on imported clinicians, so the objection that PAs are mostly trained overseas carries less weight than it first appears.
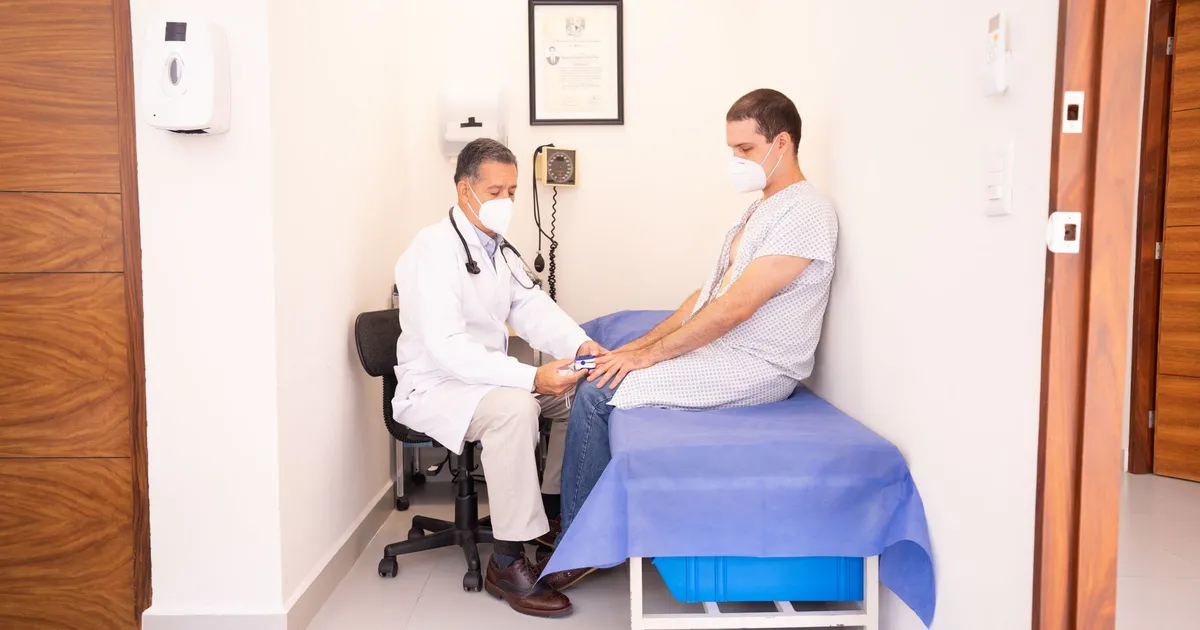
PAs are not lightly trained either. Hawke’s Bay urgent care PA Andie Cook describes a 27-month master’s programme on top of a degree and years as a US military medic. “Even though we are not a doctor, we can still see a wide breadth and depth of patients to help open and ease the pressures on the doctor,” she says.
The rules that cap the upside
The legal groundwork was laid by an Order in Council in April 2025. The operating detail sits in MCNZ’s supervision framework, and it is strict. Primary supervisors must be vocationally registered doctors. PAs can only work where onsite supervision is available and cannot be rostered solo. No supervisor may oversee more than three PAs at once.
MCNZ chairman Dr Kenneth Clark says PAs “must continue to work under a doctor’s supervision throughout their practice”.
That three-to-one cap is the number every clinic owner should model around. It answers the sharpest warning from the Royal Australasian College of Physicians, which told MCNZ in early 2026 that unlimited ratios “could potentially open up to commercial models with one doctor and many PAs”. The practical effect is that PA headcount now scales with supervising doctor headcount, not with patient demand or PA supply.
Governance lands on the employer
The framework also places overall clinical responsibility on the employing organisation, through a CMO, clinical director or clinical lead, who must confirm supervisors have the capacity and capability to do the job. That is a new compliance layer. Under the old voluntary scheme, oversight was, in the words of the 2025 Regulatory Impact Statement, “reportedly highly variable”, even though PAs were doing suturing and excisions.
Two open questions should concern boards. First, supervision time costs money. The RACP argued in 2026 for protected time of at least 0.25 FTE per PA and warned that burden was not accounted for in workforce planning. MCNZ did not mandate it, but a clinic that ignores it is betting its doctors can absorb the load. Second, indemnity between PA, supervisor and employer does not appear to have been settled in the framework as reported. Clinic owners should get that clarified with insurers before adding PAs, not after a complaint.
The doctors’ lobby isn’t finished
Opposition has been consistent. In 2024, surgeons and six other bodies urged a rethink, with surgeons warning that arm’s-length supervision could compromise safety. In 2025 the Council of Medical Colleges argued there were no PA tasks existing professions could not deliver.
Some of that is legitimate caution. Some of it is professional turf. The evidence so far favours the PAs, and the 2025 Regulatory Impact Statement found evidence of actual harm “scant”, though that partly reflects how small the workforce has stayed.
Prescribing is the real swing factor
The biggest productivity constraint is not supervision ratios. It is that PAs cannot prescribe in New Zealand, unlike in the US, UK and Canada. Every script runs back through a doctor. Cook calls prescribing rights “the next step”, and that will be the next fight.
For now, the sensible play is narrow. Rural and urgent care practices with at least one vocationally registered doctor willing to supervise should be recruiting PAs. Everyone else should do the supervision maths first. The regulation is a step forward, but the bottleneck has simply moved from the PA to the doctor standing behind them.
Sources
- RNZ: Explainer – What are physician associates, and how might they change health care? (2026-11-10)
- NZ Herald: Explainer – What are physician associates, and how might they change health care? (2026-11-09)
- RNZ: New Zealand to recognise physician associates – minister (2025-04-27)
- RNZ: Taranaki GP practice network embracing physician associates (2024-01-21)
- Medical Council of New Zealand: Annual Report 2025 (2025-06-30)
- Medical Council of New Zealand: Supervision framework for physician associates (2026)
- RACP: Submission to MCNZ on regulation of physician associates (2026-02)
- Ministry of Health: Regulatory Impact Statement on regulation of the physician associate profession (2025-05)
- NZ Doctor: Surgeons add their voice to concerns about introduction of physician associates (2024-10-18)
- RACS: Surgeons add their voice to concerns about the introduction of physician associates (2024-10-18)
- Council of Medical Colleges: Position on the regulation of physician associates (2025)
Join the discussion
Add useful context, ask a good question, or challenge an idea — keep it specific and respectful.