
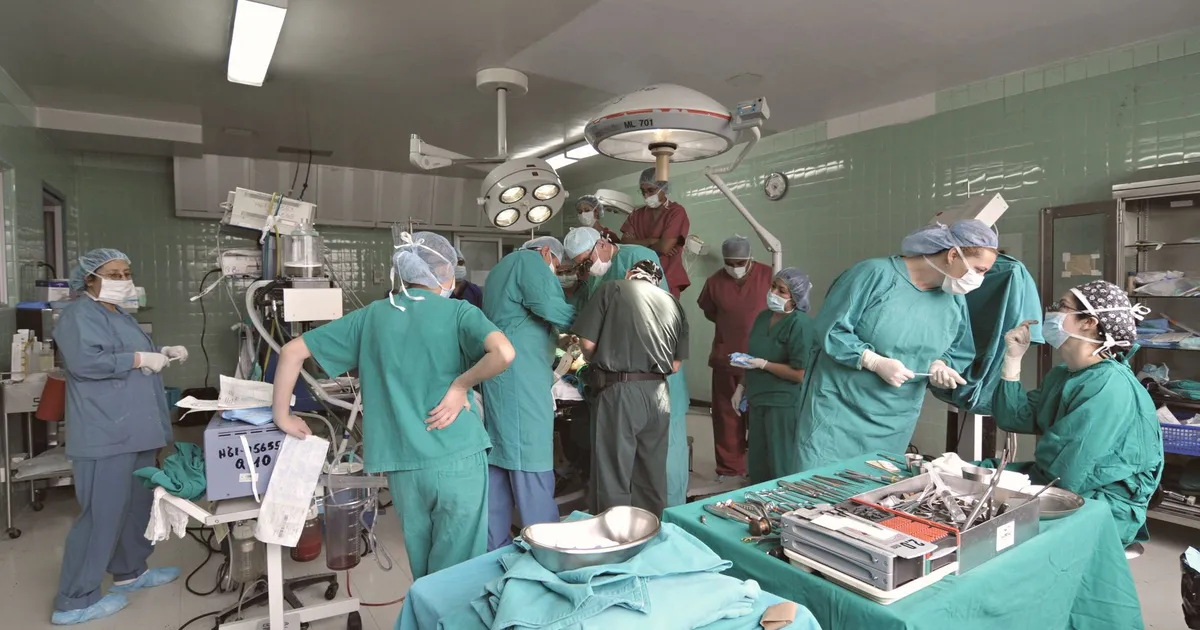
Private providers received $14.8 billion of the $31.9 billion that Health NZ and ACC spent in 2024/25, or 46.4% of the total. That figure comes from a union-commissioned report, and it should be read with that in mind. Even so, the numbers point to something the left and right should both accept. Private delivery is no longer a pressure valve bolted onto the public system. It is close to half the system.
That changes the useful question. Arguing over whether private hospitals should do publicly funded work is a debate about 2015. The live issue is whether the government buys that work like a disciplined customer, and on current evidence it does not.
The growth all went one way
The report, commissioned by the NZNO, ASMS and PSA, finds the private sector captured 80% of the $3 billion increase in combined Health NZ and ACC spending since 2022/23. “There was a $3 billion increase… and 80 percent of that went to the private sector,” researcher Edward Miller says, adding that Health NZ’s own internal advice shows outsourcing is more expensive than insourcing. Publicly delivered care grew by just $600 million.
Publicly funded elective surgery in private hospitals rose 93% over four years to more than $1 billion. This is not a sudden shift. ACC’s own data, released in 2025, showed surgical implant procedures outsourced to private hospitals climbing from 23,317 to 54,422 over the decade to 2023/24. Successive governments of both stripes built this.
Electives Boost works, at an unpublished price
Credit where it is due. Health NZ delivered 43,819 outsourced procedures in 2025/26, 11.9% ahead of its Electives Boost target. In March, Westpac Economics said the programme was “reducing wait times, with a higher share of patients receiving treatment within four months” and lifting throughput. Patients getting hips done sooner is a real result.
The problem is that nobody outside Health NZ can say what each procedure costs compared with doing it in a public theatre. In August, Health NZ signed its first long-term private hospital contracts, $300 million over six years, without disclosing the value and volume breakdown. Its 2025 outsourcing advice set out pipeline planning but no public cost-per-procedure comparison. In May, ASMS called on Te Whatu Ora to publish exactly those comparisons.
Any business owner would recognise the risk. You cannot judge value for money if you will not show anyone the price.
Three suppliers and one shared workforce
Two structural facts make that opacity more dangerous. First, the market is concentrated. Three entities control 70% of private hospital beds, and six-year contracts now anchor their expansion plans to 2032. Long contracts give private operators the certainty to invest, which is sensible. They also lock the state into a thin supplier base where its bargaining power erodes with every renewal.
Second, the workforce is the same people. Westpac warned that outsourcing “can constrain public capacity” as clinicians shift hours to better-paid private work, leaving public hospitals with the complex cases. An academic writing in 2025 argued private care “does not ‘free up a bed'” because the same limited pool of doctors and nurses works in both. ASMS found planned care treatments for the year to December 2025 were only 2% higher than the year before.
If total specialist hours are fixed, outsourcing mostly changes the address and the invoice. Paying more for the same surgeon’s time is not productivity.
What disciplined buying looks like
None of this argues for unwinding private delivery. Miller’s call to route funding back into public capacity is an ideological preference, and the record of state-run hospitals on waiting lists does not make it compelling. Back in 2024, a New Zealand Medical Journal editorial warned that blurring public and private lines overseas produced “short-term gain and long-term pain”. The answer to that is better contracts, not fewer of them.
A government that genuinely believes in markets should act like a demanding customer. That means publishing unit prices and outcome data, benchmarking private against public cost per procedure, pricing complexity so private hospitals cannot cherry-pick the easy cases, and using contract terms to grow the specialist workforce rather than just bidding for it.
For private operators, insurers and investors, the message is mixed. Public money now underwrites a large share of the sector’s revenue and growth, which is attractive. But revenue that rests on opaque procurement is political risk, and with an election close, that risk is rising. The providers who welcome transparency now will be the ones still holding contracts when the next government starts asking what $14.8 billion actually bought.
Sources
- Stuff: Private providers received $14.8b in public health funding last year, report finds (2026-10-27)
- RNZ: Private sector gets 80% of increase in public health funding, unions’ report finds (2026-10-27)
- RNZ: Private sector gets 80% of increase in public health funding – union report (2026-10-27)
- ACC: OIA response GOV-038646 – ACC elective surgery data (2025-03-21)
- Westpac Economics: Healthcare in New Zealand – the changing role of the private sector (2026-03-10)
- NZ Herald: Health NZ signs $300m six-year private hospital contracts to treat orthopaedic backlog (2026-08-13)
- ASMS: Unmet, unmeasured and unseen (2026-05)
- The Conversation: NZ’s shift to more private health care will likely raise costs and reduce quality (2025-08-31)
- New Zealand Medical Journal: The looming spectres of public-private partnerships for hospitals (2024-02-21)
Join the discussion
Add useful context, ask a good question, or challenge an idea — keep it specific and respectful.